Short answer
OAE—otoacoustic emissions—assesses the function of outer hair cells in the cochlea. It is an important objective tool in newborn and paediatric hearing screening and in broader diagnostic assessment.
But OAE is not a complete hearing test. A present OAE does not prove that the entire auditory pathway is normal, and an absent OAE does not automatically mean permanent hearing loss.
The result should be interpreted alongside outer- and middle-ear status, tympanometry, ABR and other findings.
What is OAE?
The outer hair cells of the cochlea participate in the amplification and fine tuning of sound. When they respond to acoustic stimulation, a very faint sound can be measured in the ear canal with a sensitive probe microphone.
That measurable response is the otoacoustic emission.
Kazakhstan’s current audiological-care rules include OAE as an objective method in neonatal and early-childhood hearing screening.
What does “OAE present” mean?
A clearly recorded emission supports the conclusion that outer-hair-cell function is present at the frequencies tested and that sound transmission through the outer/middle ear was adequate enough for the response to be recorded.
That is useful and reassuring information.
It does not directly measure:
- behavioural hearing thresholds;
- speech understanding;
- the entire auditory nerve/brainstem pathway;
- listening in noise;
- language development or auditory attention.
So “OAE present” should not be translated into “the whole hearing system has been completely tested.”
What does “OAE absent” mean?
An absent emission can be associated with reduced outer-hair-cell function, but that is not the only possible explanation.
The recording can also be affected by:
- middle-ear fluid;
- other conductive middle-ear problems;
- ear-canal debris or wax;
- poor probe fit;
- movement or environmental noise;
- technical recording conditions.
For that reason, a refer/absent result is a reason for follow-up rather than a diagnosis by itself.
Why middle-ear status matters
OAE depends on sound travelling through the conductive system twice: the test stimulus goes inward toward the cochlea, and the very faint emission then travels back outward to the probe microphone.
If the middle ear transmits sound poorly, the measured response may be reduced or absent even when some cochlear function is preserved.
This is why tympanometry is often valuable when interpreting OAE.
Why OAE is not an audiogram
A behavioural audiogram estimates the lowest sound level a person can reliably detect across frequencies.
OAE measures a different physiologic process—outer-hair-cell function.
Therefore OAE cannot be used on its own to create a full behavioural threshold audiogram or to assign the degree of hearing loss.
For infants who need objective threshold estimates, frequency-specific ABR and, in selected cases, ASSR are used.
Can OAE be normal when hearing is still abnormal?
Yes.
A key example is auditory neuropathy spectrum disorder. Outer hair cells may function normally, so OAE can be present, while neural transmission is disrupted and ABR is markedly abnormal or absent.
NIDCD describes this preserved-OAE/abnormal-ABR pattern as characteristic of auditory neuropathy.
That is one reason OAE alone cannot prove that the entire auditory pathway is functioning normally.
Can OAE be absent and later hearing be better than expected?
Yes, particularly when the initial result was affected by temporary middle-ear conditions or recording factors.
This is why a newborn who receives a refer result should complete the recommended re-screening and, when needed, diagnostic assessment.
Kazakhstan’s current pathway includes neonatal screening, re-screening and in-depth audiological assessment when abnormalities are identified.
OAE and ABR: how are they different?
OAE
Primarily reflects outer-hair-cell/cochlear function and is dependent on adequate sound transmission through the outer and middle ear.
ABR
Records an electrophysiologic response from the auditory pathway through the brainstem and, with diagnostic frequency-specific protocols, can estimate hearing sensitivity.
The two tests do not compete. They assess different parts of the same auditory system.
Why tympanometry matters
Tympanometry evaluates middle-ear status and eardrum mobility.
If OAE is absent and tympanometry also shows middle-ear dysfunction, that may help explain part of the result. If the middle ear appears normal and OAE is still absent, a broader diagnostic test battery becomes even more important.
When might ABR be needed after OAE?
ABR may be considered when:
- a child did not pass screening;
- there are concerns about responses to sound despite a previous OAE result;
- clinical risk factors are present;
- the child cannot complete reliable behavioural audiometry;
- OAE and observed behaviour do not agree;
- neural synchrony needs to be assessed.
The exact protocol should be selected by the clinician based on age and previous results.
Frequently asked questions
If OAE is present in both ears, does my child need no further testing?
In a routine screening pathway, that result may be sufficient at that point. But if new concerns, speech delay, risk factors or inconsistent responses appear later, an old pass does not answer the new clinical question.
Is OAE painful?
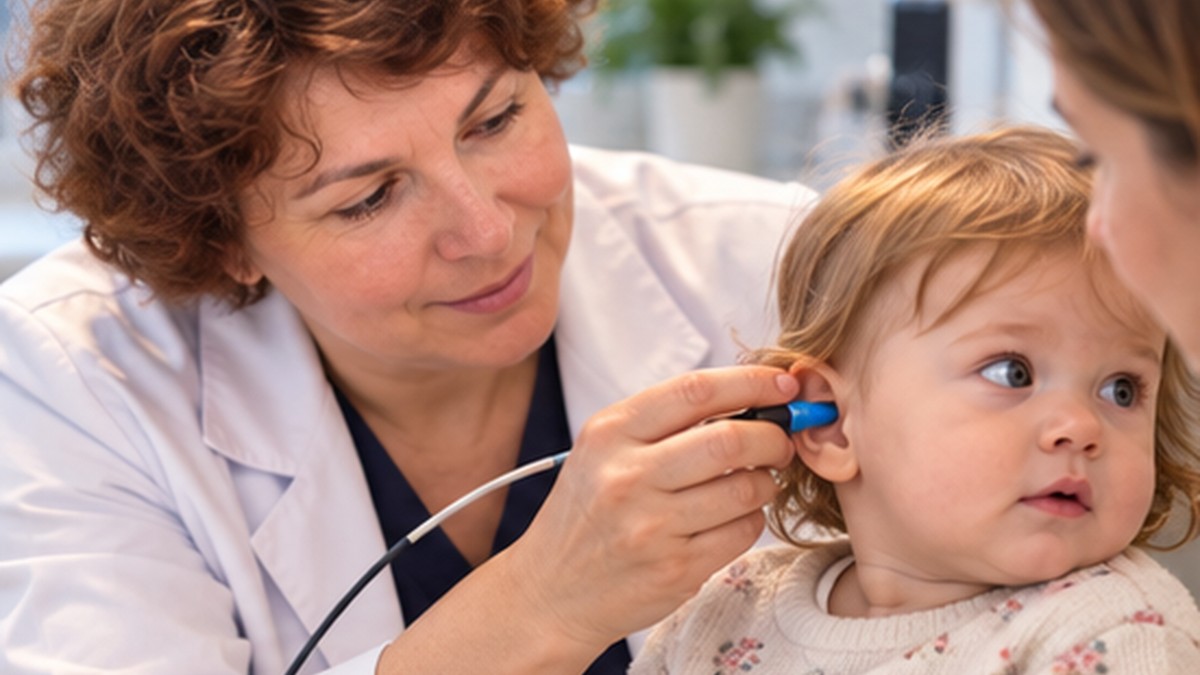
No. A small probe is placed in the ear canal, quiet sounds are presented and the response is measured.
Why can OAE fail after an ear infection?
Middle-ear changes can interfere with sound transmission and reduce the recorded emission. Middle-ear assessment and appropriate follow-up may be needed.
Can OAE show the degree of hearing loss?
No. OAE is not a full threshold audiogram.
Why do OAE if ABR has already been done?
Because OAE provides separate information about outer-hair-cell function and helps clinicians cross-check different levels of the auditory system.
OAE assessment in Almaty
Ekaterina Vladimirovna Kravchenko provides paediatric audiological assessment including OAE, tympanometry, ABR and, when indicated, ASSR.
Related pages: